Tag Archives: medical education

My Favorite Rejections

I tweeted recently about the idea of keeping a “failure resume” which was recommended by an article published in the New York Times.

If I have learned one thing in academics, it’s this – you have to develop thick skin.

Continue reading My Favorite Rejections

Success in scientific journal publication is built on a pile of rejections. For every trainee and junior faculty member out there, know that your mentors have survived countless rejections (failures) to get to where they are today.

Rather than bemoan these rejections, perhaps we should celebrate them instead. Each failure can be a learning opportunity. I dug through some old emails to find a few of my favorite rejections and happily share them below. They fall into one of two general themes.

Theme 1: “It’s not you. It’s me.”

Theme 2: “It’s not me. It’s you.”

Don’t let these rejections get you down. Good research and good writing will eventually find a home in a journal. If you get stuck, reach out to a mentor for guidance. When you see your article published finally, you can look back at those earlier rejections as badges of honor and proof that persistence pays off.

Related Posts:

Regional Anesthesia Education and Social Media

At the 2018 annual meeting of the European Society of Regional Anaesthesia and Pain Therapy (ESRA), I was invited to give a talk on regional anesthesia education and social media.  In case you missed it, I have posted my slides on SlideShare.

After my session, I was asked by ESRA to highlight some of the key points of my lecture:

Related Posts:

Why I Still Love Being an Anesthesiologist

When I first wrote “What I Love about Being an Anesthesiologist” for KevinMD in 2014, it was shared over 14,000 times!

Nearly 4 years later, I still love what I do – in fact, I think I love it even more now! My wife and I were at a party recently attended by healthcare and non-healthcare people. Of course, I was asked the inevitable questions, “What do you do?” and “What is it like?”

Here is how I answered:

Being a physician anesthesiologist is the honor of a lifetime, and it comes with a tremendous amount of responsibility. My patients rely on me to be their personal physician during surgery.  Under general anesthesia, they need me to be their voice because they can’t speak. They need me to act because they cannot protect themselves.

  • I have to understand my patients’ medical conditions.
  • I adapt my anesthetic plans to their needs.
  • I anticipate challenges that may take place during an operation.
  • I recognize problems early and prevent them when possible.
  • I react quickly and appropriately to make sure my patients make it through surgery safely with the best possible outcomes.

In the operating room, I cannot write an order and expect someone else to carry it out. I have to know how everything in my environment works, from top to bottom, so I can take the best care of my patients. I set up my own anesthetic equipment and supplies in preparation for surgery. I prepare all of the medications that I will personally administer to my patients.

I will admit that a big reason I chose this specialty was the people in it. Now my fellow physician anesthesiologists are my colleagues and mentors who continually challenge and inspire me.

I have the best job in the world:  helping patients through the stressful experience of surgery, relieving pain, and making new discoveries through research that will hopefully benefit future patients.

Related Posts:

Partnering with Patients for Patients

As an anesthesiologist, I am a physician who cares for patients when they are most vulnerable.  Under anesthesia, no one is able to call for help.  Every day patients have surgery in operating rooms all over the world, and it is the job of the physician anesthesiologist to watch over them, monitor their bodies’ responses to stress, breathe for them, provide them with pain relief, and fight for them when unexpected crises occur.  It is my job to calm the fears of my patients and families, listen to their requests, manage their expectations, and develop a plan that will provide them with the best outcome after surgery.

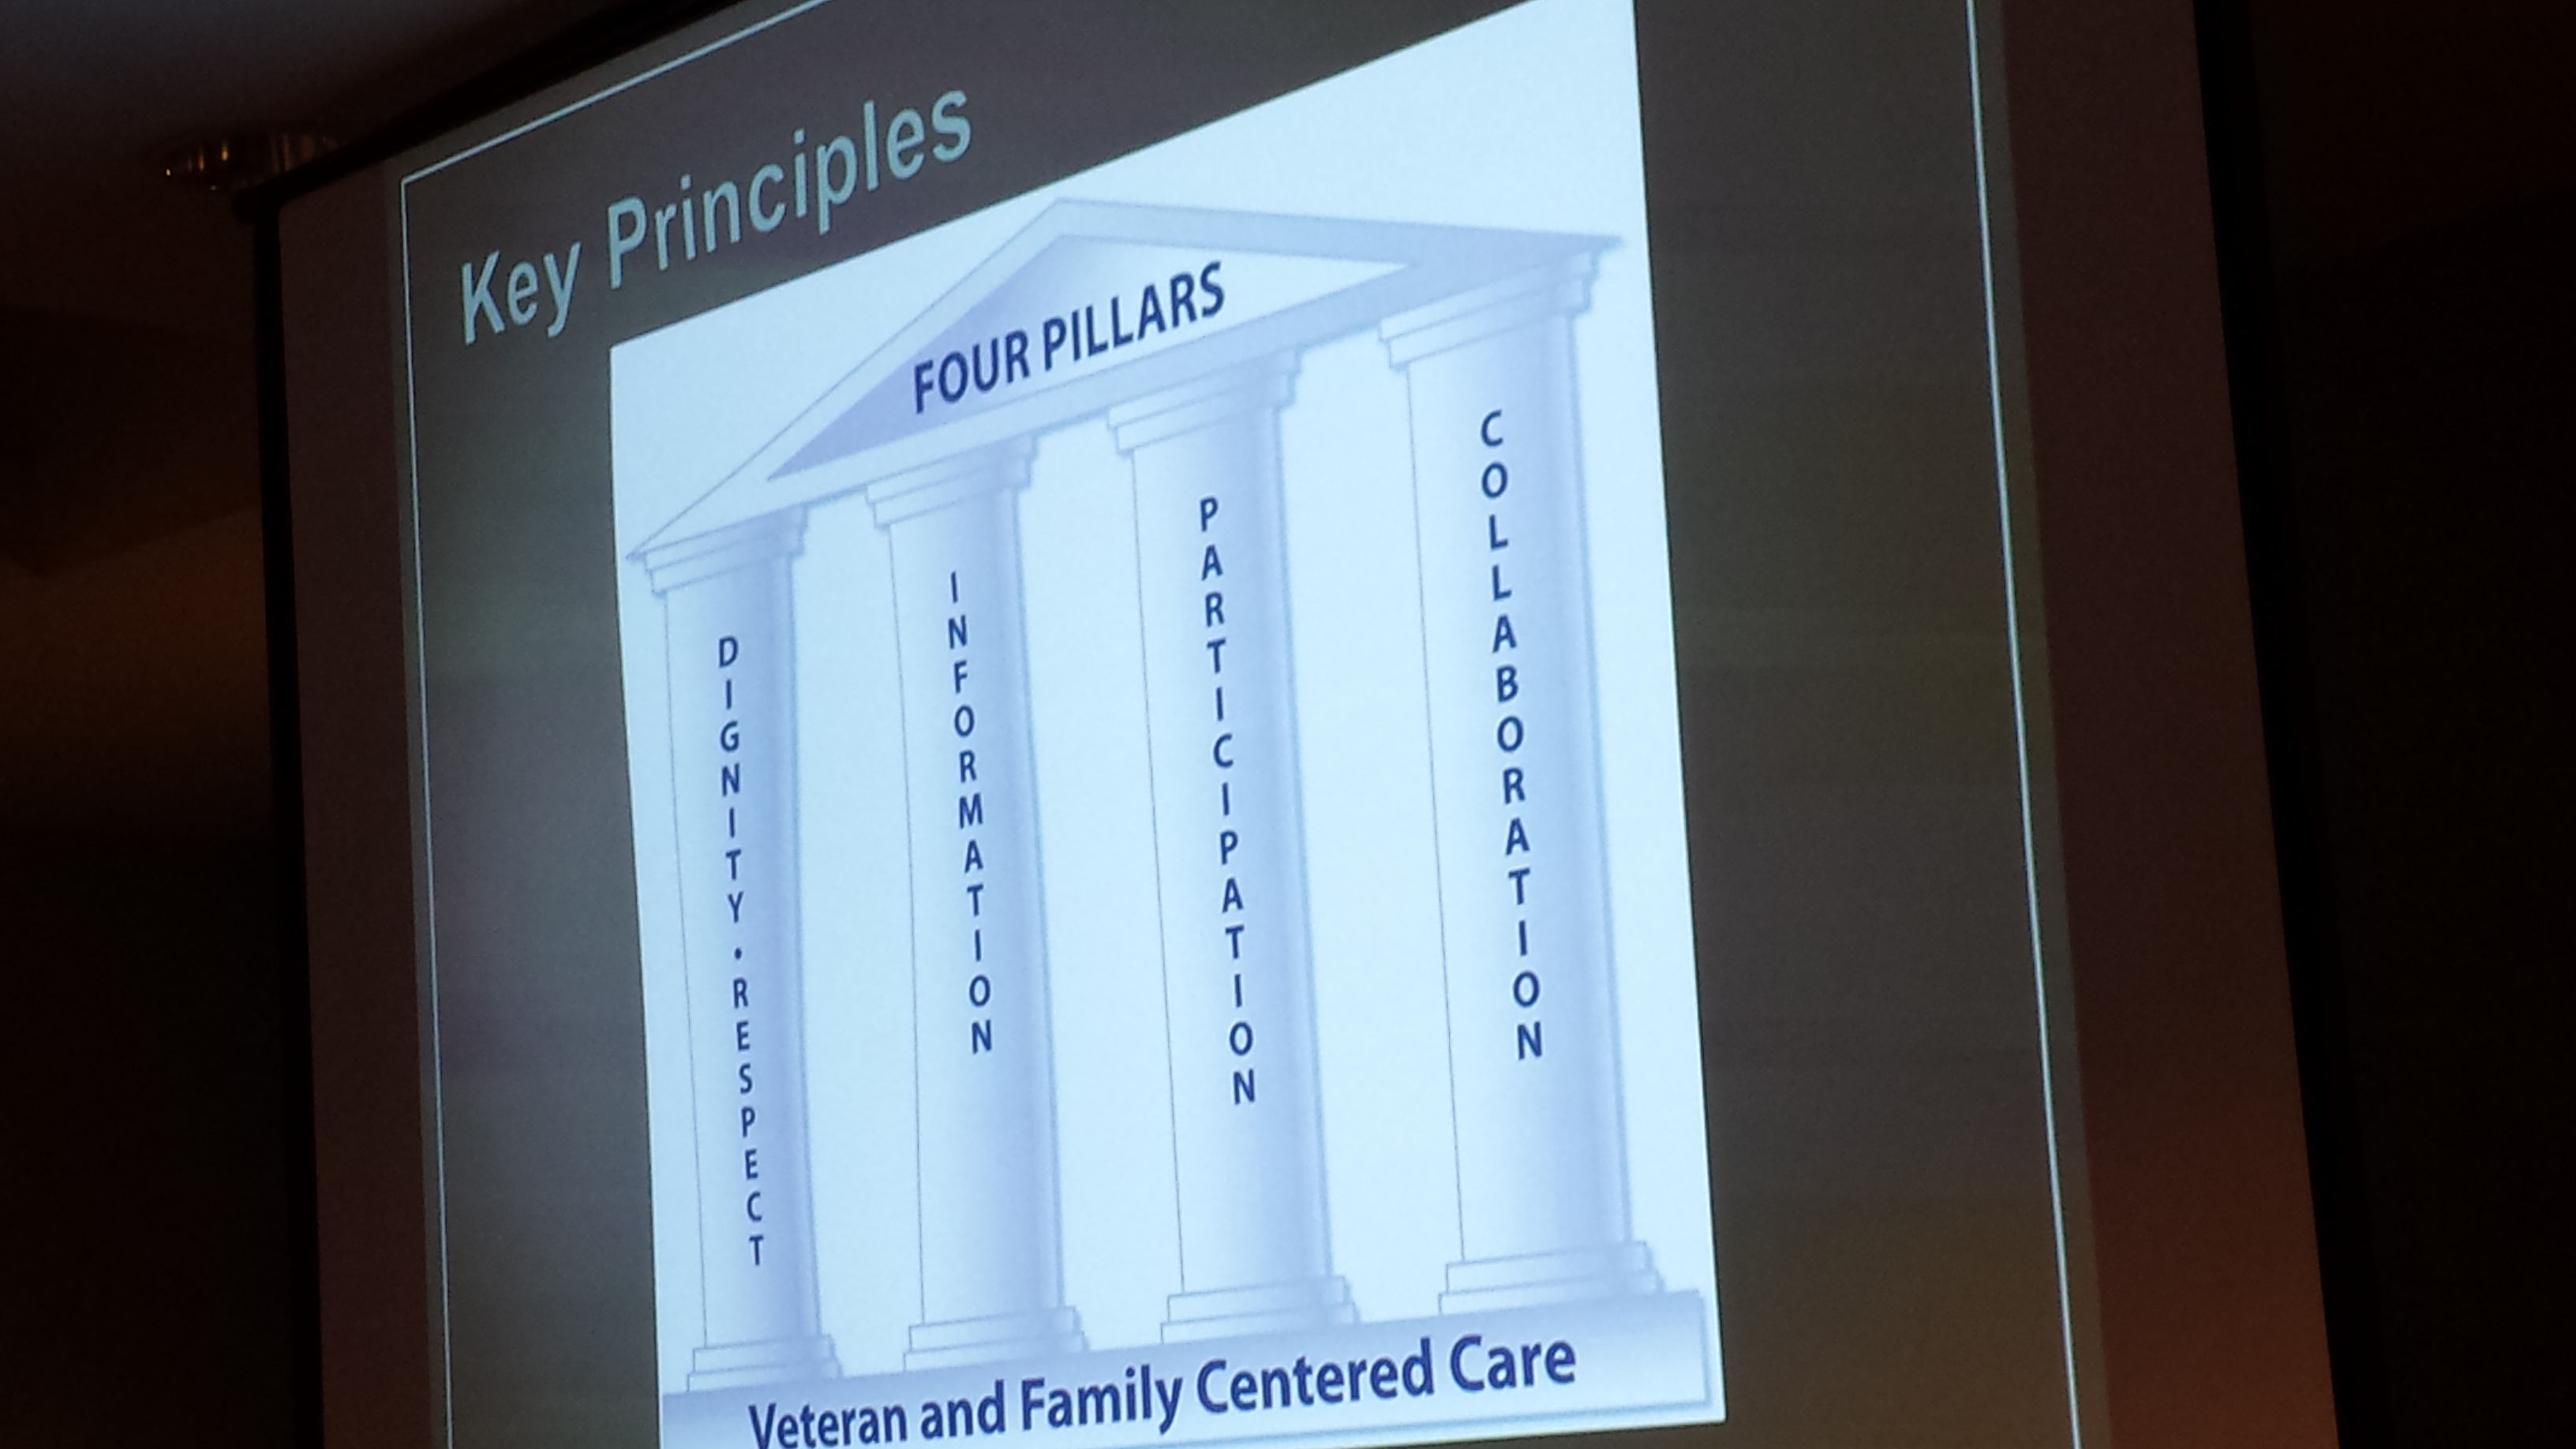
My belief in this connection between physicians, patients, and families as an anesthesiologist stretches into my administrative roles as well.  As Chief of the Anesthesiology and Perioperative Care Service and Associate Chief of Staff for Inpatient Surgical Services at the VA Palo Alto Health Care System (VAPAHCS), I am grateful for the opportunity to work with an incredible team of physicians, respiratory therapists, surgeons, advanced practice providers, technicians, and administrative staff members who are focused on our mission to provide the highest quality Veteran-centered care by leading, educating, and innovating in anesthesiology and perioperative medicine.

In order to accomplish this mission, we need the best information available to guide our decisions and a diversity of perspectives to enhance our ability to train new clinicians and explore relevant research questions.  We have been fortunate to partner with our friends and colleagues in the Veteran and Family Advisory Council (VFAC) on a number of exciting projects.  First, our Service manages the simulation center at VAPAHCS and is responsible for coordinating simulation-based training for all clinicians.  Members of VFAC have been directly involved in simulation activities, even taking on active roles as the patient or family member in standardized training scenarios, to help us educate clinicians from various disciplines and all training levels.  Debriefing after these simulation exercises gives our clinical trainees and practicing clinicians the unique perspective of real patients and family members which is essential to their professional development as modern medicine continues to progress towards a model of patient-centered care.

Once a year, our Service organizes a faculty development retreat during which we reassess our mission, vision, strategic priorities, and tactics and work on one or two big ideas.  Two years ago in 2015, we invited our VFAC partners to join us at our annual retreat to brainstorm improvement ideas related to patient-centered care in the perioperative environment, intensive care unit, and pain management.  The general theme of the retreat addressed public perception and professional reputation of anesthesiologists and the specialty of anesthesiology.  Having members of VFAC present at the retreat to share their knowledge, opinions, and questions has inspired a few subsequent improvement activities and other projects to enhance the range of services that we provide to our patients and their families.

Finally, working together with VFAC, and knowing members personally, has allowed our clinical Service to solicit feedback on a regular basis.  Not all hospitals enjoy the level of access to a community of engaged patients and families like we do at VAPAHCS.  When we revised our preoperative education materials for patients, we went to VFAC for input.  When we were critically reviewing our website to update our online patient educational materials on anesthesia and perioperative care, we presented at the VFAC meeting to get the members’ feedback and suggestions.  With their help, we have been able to improve the accessibility and readability of our online content and provide our patients and their families with useful information that can help prepare them for surgery.

We are very grateful to VFAC for its priceless contributions to our healthcare system, our patients, and our Service.  We look forward to continued collaboration on future projects!

This blog has also appeared as a featured story on the VA Palo Alto Health Care System website.

Related Posts:

Tips for Live Tweeting a Meeting

Live tweeting during a scientific conference offers many benefits. For attendees at the meeting, it allows sharing of learning points from multiple concurrent sessions. This also decreases the incidence of “FOMO (Fear of Missing Out)” since you can only be in one session at any given time but can learn vicariously through others. For your Twitter community outside the meeting venue, your live tweeting can help to disseminate the key messages from the conference to a broader audience and ultimately may facilitate changes in clinical practice.

Check out these “Ten Simple Rules for Live Tweeting at Scientific Conferences” and Marie Ennis-O’Connor’s “15 Tips for Live Tweeting an Event” for a comprehensive overview of this subject.

Here are a couple of my own general rules to tweet by:

  1. Register your scientific conference hashtag on Symplur. This gives you access to free analytics and transcript services for a limited time.
  2. Be sure to use the correct conference hashtag and include it in all your tweets related to the conference. This is probably included in your conference materials or emails from the organizer. The hashtag allows others to easily find your tweets related to the conference and include your tweets in transcript summaries after the conference is over.
  3. Go for quality and not quantity. It is too difficult (and unnecessary) to give a phrase-by-phrase reproduction of a speaker’s entire lecture. Remember that you are primarily in attendance to learn, so make sure you spend most of your time listening and not tweeting. Consider summarizing two or three salient points into one tweet or tweeting photos of slides with a short commentary to provide context to your Twitter community.
  4. Give credit where credit is due. Do a little homework before tweeting. If a speaker has a Twitter handle, include it in your tweet. If the speaker references a relevant article, find the link and include it in your tweet. These elements make your tweet more informative to the reader and may increase the likelihood of its being retweeted or generating further conversation on Twitter.
  5. Don’t say anything in a tweet that you wouldn’t say to someone in public. Healthy debate is one of the best parts of scientific conferences, but keep the discussion on Twitter clean and professional and of course protect patient privacy and confidentiality.

Related Posts:

A New Era for Regional Anesthesiology and Acute Pain Medicine

It has finally happened–the inaugural class of ACGME-accredited Regional Anesthesiology and Acute Pain Medicine (RAAPM) fellowships has been announced, marking the beginning of a new era.

Congratulations to the following 9 programs that now are the first accredited fellowship programs representing this subspecialty in the United States:

  1. Stanford University
  2. Cedars-Sinai Medical Center
  3. University of California, San Francisco
  4. Massachusetts General Hospital
  5. Brigham and Women’s Hospital
  6. Montefiore Medical Center/Albert Einstein College of Medicine
  7. Icahn School of Medicine at Mount Sinai/St. Luke’s-Roosevelt Hospital
  8. Duke University Hospital
  9. Vanderbilt University Medical Center

Accreditation is immediate and retroactive to the current 2016-17 academic year. This announcement represents a tremendous achievement in anesthesiology training and medical education in general.  Nearly 4 years ago, at our spring RAAPM fellowship directors meeting in 2013, I was appointed to lead the task force that would eventually make contact with the ACGME to request consideration for accreditation of our subspecialty fellowship programs. After submitting the 161-page letter to ACGME, we waited nearly a year to receive a response, and it was positive. The next 2 years were spent drafting the program requirements that would eventually be used as the basis for fellowship design and evaluation. This was an iterative process with multiple revisions based on solicited feedback and public commentary.

When the application period opened for the first time ever in October 2016, programs interested in applying had less than 2 months to prepare their program information forms and other materials, have them reviewed and approved by their local graduate medical education offices, and submit to ACGME in time for the 2017 spring review.

These 9 accredited programs have embarked on a brave new path, but it will not be an easy one. Their programs will be reviewed periodically to evaluate adherence to the program requirements and the quality of fellowship training, and deficiencies identified will need to be resolved or face loss of accreditation. However, their commitment to maintaining accreditation represents, in my opinion, a commitment to their fellows that they will provide a training experience that can be held as a benchmark for all programs.

We need our fellowship training programs to develop leaders in regional anesthesiology and acute pain medicine who can catalyze changes in healthcare that will improve patient outcomes and experience. Today, we have taken a huge step forward.

Related Posts:

The “Top 10” Regional Anesthesia Articles of 2016

I was recently asked to provide a list of my “Top 10” regional anesthesia research articles from 2016 and not to include my own. So for what it’s worth (not much!), I’m sharing them below in no particular order.

In my humble opinion, these articles from 2016 have already influenced my clinical practice, taught me to look at something differently, or made me think of a new research question.

Trends in the Use of Regional Anesthesia: Neuraxial and Peripheral Nerve Blocks. Reg Anesth Pain Med. 2016 Jan-Feb;41(1):43-9. doi: 10.1097/AAP.0000000000000342.

The Second American Society of Regional Anesthesia and Pain Medicine Evidence-Based Medicine Assessment of Ultrasound-Guided Regional Anesthesia: Executive Summary. Reg Anesth Pain Med. 2016 Mar-Apr;41(2):181-94. doi: 10.1097/AAP.0000000000000331.

Teaching ultrasound-guided regional anesthesia remotely: a feasibility study. Acta Anaesthesiol Scand. 2016 Aug;60(7):995-1002. doi: 10.1111/aas.12695.

Paravertebral block versus thoracic epidural for patients undergoing thoracotomy. Cochrane Database Syst Rev. 2016 Feb 21;2:CD009121. doi: 10.1002/14651858.CD009121.pub2.

Perineural versus intravenous dexamethasone as adjuncts to local anaesthetic brachial plexus block for shoulder surgery. Anaesthesia. 2016 Apr;71(4):380-8. doi: 10.1111/anae.13409.

Continuous Popliteal Sciatic Blocks: Does Varying Perineural Catheter Location Relative to the Sciatic Bifurcation Influence Block Effects? A Dual-Center, Randomized, Subject-Masked, Controlled Clinical Trial. Anesth Analg. 2016 May;122(5):1689-95. doi: 10.1213/ANE.0000000000001211.

A randomised controlled trial comparing meat-based with human cadaveric models for teaching ultrasound-guided regional anaesthesia. Anaesthesia. 2016 Aug;71(8):921-9. doi: 10.1111/anae.13446.

Adductor Canal Block Provides Noninferior Analgesia and Superior Quadriceps Strength Compared with Femoral Nerve Block in Anterior Cruciate Ligament Reconstruction. Anesthesiology. 2016 May;124(5):1053-64. doi: 10.1097/ALN.0000000000001045.

A radiologic and anatomic assessment of injectate spread following transmuscular quadratus lumborum block in cadavers. Anaesthesia. 2017 Jan;72(1):73-79. doi: 10.1111/anae.13647.

Regional Nerve Blocks Improve Pain and Functional Outcomes in Hip Fracture: A Randomized Controlled Trial. J Am Geriatr Soc. 2016 Dec;64(12):2433-2439. doi: 10.1111/jgs.14386.

Related Posts:

Tips for Reading a Clinical Research Article

It is getting more and more difficult to keep up with newly published articles even just in one medical subspecialty.  With so much to read, from background articles for research papers to articles for journal club to manuscript assignments as a peer reviewer, it is important to be efficient and attack every scientific article or manuscript strategically.

Clinical research is my focus area, but the following updated tips for interpreting a journal article may apply to other areas of research as well.

Background:  Do the authors summarize previously published studies leading up to the present study?  What don’t we already know about this topic?

  1. Do the authors do a good job justifying the reason for the study?  This should not be lengthy if there is clearly a need for the study.
  2. Do the authors present a hypothesis?  What is it?
  3. What is the primary aim/objective of the study?  Do the authors specific secondary aims/objectives?

Study Design:  Do the authors explicitly state the design used in the present study?  If so, what is it?

Retrospective (“case-control study”):  Starts with the outcome then looks back in time for exposure to risk factors or interventions

  1. Can calculate odds ratios to estimate relative risk.
  2. Cannot calculate risk/incidence (not prospective).

Cross-sectional (“prevalence study”):  Takes a snapshot of risk factors and outcome of interest at one point in time or over a specific period of time

  1. Can calculate prevalence.
  2. Cannot calculate risk/incidence (not longitudinal).

Prospective:  Gold standard for clinical research–may be observational or interventional/experimental.  Check if the study is prospectively registered (e.g., clinicaltrials.gov) because most journals expect this.

Observational (“cohort study”)

  1. May or may not have a designated control group (can start with defined group and risk factors are discovered over time such as the Framingham Study).
  2. Can calculate incidence and relative risk for certain risk factors.
  3. Identify causal associations.

Interventional/Experimental (“clinical trial”)

  1. What is the intervention or experiment?
  2. Is there blinding?  If so, who is blinded:  single, double, or triple (statistician blinded)?
  3. Are the groups randomized?  How is this performed?
  4. Is there a sample size estimate and what is it based on (alpha and beta error, population mean and SD, expected effect size)?  This should be centered around the primary outcome.
  5. What are the study groups?  Are the groups independent or related?
  6. Is there a control group such as a placebo (for efficacy studies) or active comparator (standard of care)?

Measurements:  How are the outcome variables operationalized?  Check the validity, precision, and accuracy of the measurement tools (e.g., survey or measurement scale).

  1. Validity:  Has the tool been used before?  Is it reliable?  Does the tool make sense (face validity)?  Is the tool designed to measure the outcome of interest (construct validity)?
  2. Precision:  Does the tool hit the target?
  3. Accuracy:  Are the results reproducible?

Analysis:  What statistical tests are used and are they appropriate?  How do the authors define statistical significance (p-value or confidence intervals)?  How are the results presented in the paper and are they clear?

  1. Categorical variables with independent groups:  1 outcome and 2 groups = Chi square test (exact tests are used when n<5 in any field); multiple outcomes or multiple groups = Kruskal Wallis (with one-way ANOVA and post-hoc multiple comparisons test (e.g., Tukey-Kramer).
  2. Continuous variables with independent groups:  1 outcome and 2 groups = Student’s t test (if normal distribution) or Mann-Whitney U test (if distribution not normal); multiple outcomes or multiple groups = ANOVA with post-hoc multiple comparisons testing; multiple outcomes and multiple groups = linear regression.
  3. Continuous variables with related groups:  paired t test or repeated-measures ANOVA depending on the number of outcomes and groups.
  4. Are the results statistically significant?  Clinically significant?
  5. Do the results make sense?

Conclusions:  I personally tend to skip the discussion section of the paper at first and come up with my own conclusions based on the study results; then I read what the authors have to say later.

  1. Did the authors succeed in proving what they set out to prove?
  2. Read the discussion section.  Do you agree with the authors’ conclusions?
  3. What are possible future studies based on the results of the present study and how would you design the next study?

Related Posts:

To the Next Generation of Physician Leaders

I was recently invited to visit an academic anesthesiology department to speak to the residents about becoming a leader (see SlideShare). In addition to recognizing the honor and privilege of addressing this important topic with the next generation of physician anesthesiologists, I had two other initial thoughts: 1) I must be getting old; and 2) This isn’t going to be easy.

Balloon FiestaI came up with a short list of lessons that I’ve learned over the years. While some examples I included are anesthesiology-specific, the lessons themselves are not. Please feel free to edit, adapt, and add to this list; then disseminate it to the future physician leaders who will one day take our places.

  1. First and foremost, be a good doctor. Always remember that we as physicians take an oath. In the modern version of the Hippocratic Oath commonly recited at medical school graduations today, we say, “May I always act so as to preserve the finest traditions of my calling and may I long experience the joy of healing those who seek my help.” As a physician anesthesiologist, we care for the most vulnerable of patients—those who under anesthesia cannot care for themselves. Examples of anesthesiologists who do not honor their calling exist in the news and even scientific journals, but we cannot follow this path. 


  2. Define your identity. We live in the era of the “provider,” and this sometimes causes role confusion from the perspective of our patients. We also don’t tend to do ourselves any favors. How many times have you heard someone say, “Hi I’m [first name only] with anesthesia”? According to the American Society of Anesthesiologists newsletter, approximately 60% of the public may not know that physician anesthesiologists go to medical school. While every member of the anesthesia care team plays a crucial role, the next level of non-physician provider in this model has one-tenth the amount of clinical training when compared to a physician anesthesiologist at graduation. I’ve written before about what I love about being an anesthesiologist, and being the physician whom patients trust to keep them safe during surgery is a privilege which comes with a great deal of responsibility.
  3. Consider the “big picture.” The health care enterprise is constantly evolving. Today, the emphasis is on value and not volume. Value takes into account quality and cost with the highest quality care at the lowest cost being the ultimate goal. The private practice model of anesthesiology has changed dramatically in the last few years with the growth of “mega-groups” created by vertical and horizontal integration of smaller practices and sometimes purchased by private investors. In this environment, physician anesthesiologists and anesthesiology groups will have to consider ways they can add value, improve the patient experience, and reduce costs of care in order to stay relevant and competitive.
  4. Promote positive change. Observe, ask questions, hypothesize solutions, collect data, evaluate results, draw conclusions, and form new hypotheses—these are all elements of the scientific method and clinical medicine. These steps are also common to process improvement, making physicians perfectly capable of system redesign. The key is establishing your team’s mission and vision, strategic planning and goal-setting, and regularly evaluating progress. Books have been written on these subjects, so I can’t do these topics justice here. In my opinion, physicians offer an important and necessary perspective that cannot be lost as healthcare becomes more and more business-like.
  5. Be open to opportunities. Thomas Edison said, “Opportunity is missed by most people because it is dressed in overalls and looks like work.” I have written previously about the merits of saying yes. As a resident or new staff physician, it often seems impossible to get involved. However, most hospital committee meetings are open to guests. Consider going to one that covers a topic of interest and volunteer for a task if the opportunity presents itself. In addition, many professional societies invite members to self-nominate for committees or submit proposals for educational activities at their annual meetings.
  6. IMG_7673Thank your team. Taking the first steps on the path to leadership is not going to be easy. There will be many obstacles, not the least of which is time management. A high-functioning healthcare team of diverse backgrounds, skills, and abilities will accomplish much more than what an individual can do alone. Celebrate team wins. Respect each team member’s opinion even when it differs from yours.

A good leader should earn the trust of his or her team every day.

Related Posts:

Why Doctors Should Be on Twitter

I am a physician, clinical researcher, and educator.

I am also on Twitter and tweet under the handle @EMARIANOMD.

Naturally you may ask:  “How does Twitter fit into a physician’s academic career?”  Some of the benefits that Twitter offers doctors have been described previously by Dr. Brian Secemsky and Dr. Marjorie Stiegler among others.  Here are a few reasons of my own:

  • Global Interaction:  Through Twitter I interact with people from around the world with similar interests.  Participating in Twitter chats like #healthxph or #hcldr can foster innovative ideas that may lead to research questions or other educational opportunities.  For example, by tweeting on #kneereplacement, I was invited by orthopedic surgeon, Dr. Brian Hatten, to revise the anesthesia information page on his site, My Knee Guide, an incredible online portal for people considering or undergoing knee replacement surgery.
  • Search Optimization:  On multiple occasions, I have found research articles that my traditional PubMed searches have missed through the tweets posted by colleagues.  I have even been able to relocate certain articles faster on Twitter than PubMed when I know they have been tweeted.  Researchers can think of hashtags (starting with “#”) essentially like keywords in the academic world.  I periodically check #anesthesia, #meded, #pain, and #kneereplacement for new articles related to my research interests.
  • Lifelong Learning:  When I was in training, I used to peruse the pages of JAMA and New England Journal of Medicine (NEJM) in addition to my own specialty’s journals.  Today, it’s difficult to even keep up with new articles just in my own subspecialty.  Now I follow JAMA and NEJM on Twitter.  By following journals, professional societies, and colleagues with similar interests, I honestly feel that my breadth of knowledge has increased beyond what I would have acquired on my own.
  • Research Promotion:  As a clinical researcher, my hope is that my study results will ultimately affect the care of patients.  Sadly, the majority of traditionally-published scientific articles will not be read by anyone besides the authors and reviewers.  Through Twitter, I can alert my followers when our research group publishes an article.  I also get feedback and “peer review” from colleagues around the world.  After a recent publication that I tweeted, I received comments from anesthesiologists in Canada and Europe within an hour!
  • Enriched Conference Experience:  A growing trend at medical conferences is “live-tweeting” the meeting.  One of my own issues when I attend or present at conferences is that I feel like I miss much of the meeting due to scheduling conflicts.  By living vicariously through my colleagues’ tweets at #ASRASpring15 for example, I can pick up pearls of wisdom from speakers in other sessions even while sitting in a different hall.  I can also “virtually” attend conferences by following tweets under the hashtags of meetings like #PCP15 in the Philippines  in the comfort of my own home.

I often get asked:  “Does anyone really care if I tweet what I eat for breakfast?”  Probably not.  The truth is that you don’t have to tweet anything at all if you don’t want to.   Up to 44% of Twitter accounts have never sent a tweet.   Of course, to be a physician actively engaged on Twitter requires respect for patient privacy and professionalism.  I recommend following Dr. John Mandrola’s 10 rules for doctors on social media.

In an interview during Stanford’s Big Data in Biomedicine Conference (video below), I had a chance to explain why I tweet.  I’ll admit that getting started is intimidating, but I encourage you to try it if you haven’t already.   I promise that you won’t regret it, and chances are that you’ll be very happy you did.  If you’re still too worried to take the leap, I suggest reading these tips from Marie Ennis-O’Connor to boost your confidence.  At least sign up, reserve your handle, and observe.

Observation is still a key part of the scientific method.

Related Posts: